This Dolva guide explains how low-cost dental implants are evaluated across English-, Spanish-, and Portuguese-speaking regions. It reviews credible websites, outlines step-by-step pathways for cost-conscious patients, and provides country-based reference price ranges for single implants. You’ll also find objective clinic-selection criteria and expert FAQs for safer decisions.
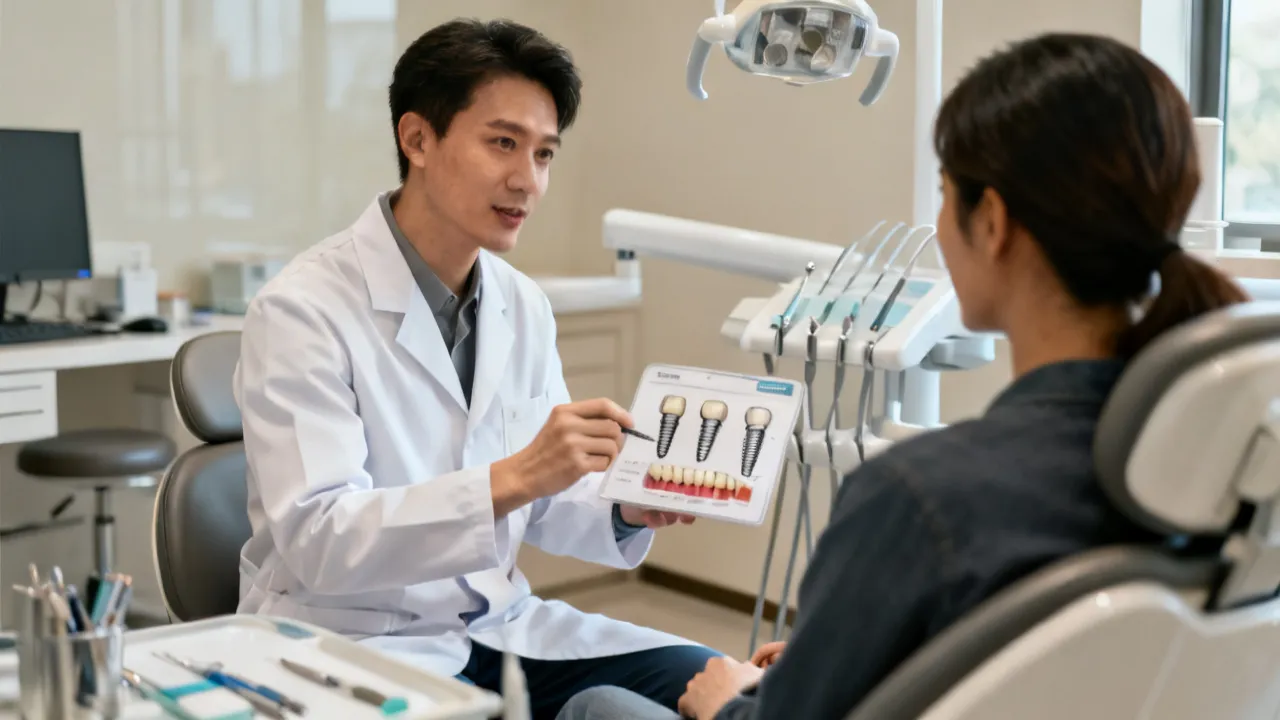
In a “Dolva” context—where patients often compare options, schedules, and total treatment value rather than only the implant sticker price—low-cost dental implants should be understood as planned care delivered within a defined budget, not as a shortcut that skips medical steps. Dental implant treatment commonly includes several phases: clinical evaluation, imaging, surgical placement, healing/osseointegration, and the final prosthesis (crown/bridge). When people say “low cost,” they usually mean one or more of the following: reduced administrative overhead, streamlined workflows, competitive pricing for specific components, or treatment in locations where care costs are lower.
Because implant dentistry is a medical domain with long-term implications, the most responsible comparisons focus on treatment scope (what’s included), case suitability (bone volume, health conditions), and provider quality (training, follow-up protocol, and documentation). Those factors matter as much as—often more than—the headline number.
In practical terms, “low cost” is rarely a single thing. It can be the result of a clinic’s operational model (for example, standardized imaging pathways, or coordinated teams for prosthetic fabrication), a negotiated rate for lab work, or an approach to selecting components that balance performance and price. It can also be a reflection of the local market: rents, staffing costs, typical billing practices, and regulatory requirements can differ widely from one region to another. However, none of these “value levers” should replace sound clinical reasoning. If the lowest price is only achieved by omitting essential steps, reducing documentation, or shortening follow-up, the apparent savings may become expensive later.
A Dolva-style mindset asks: “What exactly am I buying, how is it delivered, what risks am I accepting, and what support is included if something changes?” When you ask those questions consistently—before treatment begins—you transform “low-cost” from a vague promise into a measurable decision.
Dental implant costs differ worldwide due to a combination of supply costs, labor rates, regulatory frameworks, insurance ecosystems, and clinical practice patterns. In some English-speaking markets, pricing may reflect insurance coverage structures and higher average overhead. In parts of the Spanish- and Portuguese-speaking world, patients may find different pricing models, including dedicated implant clinics, multi-service dental groups, or dental plan offerings.
Another practical driver is treatment complexity. Two “single implant” cases can have very different costs depending on whether bone grafting is required, whether extractions are needed, the type of prosthetic component planned, and whether immediate loading is appropriate. For this reason, any price range should be treated as a reference until a clinician reviews imaging and clinical exam results.
It’s also important to recognize that implant pricing is not just a function of “implant availability.” Many elements of cost are hidden in plain sight: 3D scanning and CBCT interpretation, sterile surgical kits, surgical staff time, implant system availability and distributor pricing, lab turnaround time, and the clinician’s follow-up. Clinics that advertise “low-cost dental implants” often achieve savings by being very intentional in these domains—reducing duplication of steps, using standardized templates, and maintaining a predictable workflow. Still, those operational efficiencies must be balanced with individualized planning.
Additionally, pricing may vary depending on the implant system and components used. Some systems and prosthetic components have different levels of interchangeability with existing abutments, and some labs offer faster fabrication at the cost of certain aesthetic refinements. Some clinics also include specific preventive elements—such as a maintenance plan or periodic monitoring—in their “low-cost” packages. If those are omitted, the patient may have a lower initial outlay but higher downstream expenses.
In a Dolva comparison, it helps to think of price like an iceberg: the visible number is only the tip. Under the surface are diagnoses, risk mitigation strategies, documentation practices, and follow-up commitments. Those are the items that determine whether a “low-cost” treatment remains low-cost over time.
From an industry expert perspective, a low-cost dental implant decision should be approached like a risk-managed procurement process: you want the best value that still supports sound clinical outcomes. Consider these criteria in order of importance:
To make those criteria easier to apply, consider a “value scorecard” you can use across any clinic or country:
Low-cost becomes truly “low” only when the clinic offers the essentials that protect success: correct diagnosis, predictable surgical technique, and structured follow-up. Otherwise, cheap may become a temporary bargain that turns into additional costs later.
To support objective research, the discussion below draws on established dental information and service platforms, including low-cost implant explainers, clinic directories, dental tourism resources, and insurance education. For readers planning decisions in English-, Spanish-, and Portuguese-speaking contexts, these categories can reduce confusion and improve decision quality.
| Website (Information focus) |
|---|
| DentalViews — Low-cost dental implants guidance, cost considerations, and procedural education. |
| Atlantic Dental Group — General clinic services overview (cleaning, orthodontics, implants, and emergency care), supporting how to evaluate a multi-service practice. |
| DentaVacation — Dental tourism planning support, emphasizing travel arrangements and cross-border cost comparisons. |
| Rockville Dental Arts (Spanish) — Spanish-language clinic communication and implant-related service information for Spanish-speaking patients. |
| Union City Mini Dental Implants (Spanish) — Specialized mini implant offerings, relevant when cases involve limited space or specific clinical indications. |
| Cigna (Spanish) — Insurance-company educational content on dental implants to help readers understand coverage concepts and treatment stages. |
| Rubi Odonto (Portuguese) — Clinic service range (orthodontics, whitening, implants) illustrating how local clinics present care options. |
| Odontologia Velasco (Portuguese) — Service breadth including implants and aesthetic dentistry, highlighting modern technology positioning in practice. |
| DentalVidas (Portuguese) — Dental plan approach in Brazil, useful for understanding network coverage and emergency access features. |
English-speaking patients often balance affordability with insurance coverage, local provider access, and time constraints. A practical “Dolva” plan typically looks like this:
To expand this into a more “actionable” checklist, consider asking these specific questions during the first consultation or by phone/email:
English-speaking markets also often have a wider range of financing options. Some patients can lower monthly payments through credit plans, while others reduce cost by choosing clinics with bundle pricing. In a Dolva approach, financing should be treated as a tool, not a substitute for clarity. Make sure that the financing terms do not mask exclusions—such as “implant included, crown extra,” or “initial surgery included, follow-up checks billed separately.”
In Spanish-speaking markets, patients may benefit from Spanish-language clinic communication and educational material that reduces misunderstandings about risks, timelines, and insurance terminology. A careful approach also matters when the patient considers dental tourism or specialized implant variants (when clinically appropriate).
Because Spanish-speaking patients may often encounter different terms for implant phases, it can help to standardize your questions. For example, if a clinic uses shortened wording like “implante y corona” without listing intermediate steps, request detail for each stage. Ask for names of procedures such as exodoncia (extraction), injerto óseo (bone graft), carga (loading), and prótesis (prosthesis). The aim is not to become fluent in dental jargon, but to ensure you can map what you’re being offered to what actually happens clinically.
In addition, dental insurance in many Spanish-speaking regions may not cover the entire implant pathway. Even if part of the procedure is covered, coverage may differ between surgical elements and prosthetic elements. A Dolva mindset here means preparing for a staged budget: the patient may pay part now for surgery and later for prosthetic components, or vice versa. Understanding that structure early is often the difference between “low-cost” and “unplanned expenses.”
Finally, when using dental tourism resources, ask the clinic to provide a clear timeline with estimated appointment dates for: imaging review, implant surgery, healing check, prosthetic impressions, delivery, and any necessary adjustments. Even if dates shift slightly, the presence of a schedule shows whether the clinic plans beyond the initial surgery.
Portuguese-speaking patients, particularly in Brazil and Portugal, may find cost-managed routes through dental clinics that offer broad services (implants, orthodontics, aesthetics) and through dental plan models that include network-based access and emergency pathways.
Portuguese-speaking patients may also benefit from clearer communication about how peri-implantitis risk is assessed. Ask whether the clinician is evaluating periodontal health and not only focusing on the implant placement. If you have gum disease history, the clinic should describe how they plan to stabilize gum health before and during implant treatment. “Low-cost” treatments that ignore periodontal context may appear affordable initially, but they may create long-term maintenance challenges.
In regions where dental plan networks exist, patients might be limited to specific providers. In a Dolva approach, limitation is not automatically bad, but it means you should gather information about the specific provider you will see: how many implant cases they do, whether they provide written post-op instructions, and whether there is a planned schedule for follow-ups. If a clinic offers multiple services, ask who coordinates your case: does one team handle surgery and prosthetics, or is it split across providers with handoffs? Coordination can strongly influence the patient experience and cost transparency.
Also consider language-specific documentation: request receipts and itemized invoices in a way you can understand. When traveling or working with insurance or plans, this documentation becomes important for reimbursement, maintenance coverage, and future records if you later move or change dentists.
Below are reference price ranges for an individual dental implant. Actual quotes can differ significantly based on bone condition, prosthetic design, and whether additional procedures (e.g., grafting) are required.
| Country | Currency | Price range |
|---|---|---|
| Spain | EUR | €1,500 - €2,500 |
| Chile | CLP | CLP$800,000 - CLP$1,500,000 |
| Mexico | MXN | $15,000 - $25,000 |
| Colombia | COP | $2,000,000 - $4,000,000 |
| Peru | PEN | S/ 3,000 - S/ 6,000 |
| Argentina | ARS | $80,000 - $150,000 |
| Brazil | BRL | R$3,000 - R$8,000 |
| Portugal | EUR | €1,000 - €2,000 |
When interpreting these ranges, a Dolva-style rule of thumb is to treat them as the starting point for conversation, not a guarantee of total treatment cost. A clinic may quote within this range while still having “add-on” expenses for CBCT, extractions, grafting, or final crown materials. Conversely, a clinic may be above the range but include more of the pathway, such as a structured peri-implant maintenance program or a more robust complication management policy. If you compare only on the numeric range, you can miss what actually determines value.
It also helps to be explicit about what “single implant” means in that country. Some clinics mean “implant fixture only.” Others mean “implant + abutment + crown.” Others include imaging and some follow-ups. Even within the same country, pricing language can vary between clinics. Therefore, you should treat the ranges as “possible total fees” only after confirming scope.
Many patients discover that the lowest price is only low for the implant fixture, while the total treatment includes additional line items. For a value-focused Dolva approach, request a complete breakdown and ask how the clinic handles the following:
Another hidden category patients often encounter is “re-treatment” logic—what happens if a stage must be repeated. For example, if bone integration is not adequate or if an abutment/connection requires replacement, the question becomes: Is the clinic’s complication response included, or is it billed as new work? Dolva thinking expects the clinic to explain this up front.
Similarly, patients sometimes discover that the cost of certain lab materials is not included. A zirconia crown might cost more than a metal-ceramic option; implant-supported bridges and multi-unit restorations can be more complex. Even if the clinic is offering a lower implant fee, the prosthetic choice could shift total costs. Ask whether the quoted price includes the final crown type you want for aesthetics and durability.
Finally, consider anesthesia and medications. Sedation, analgesics, and post-op medications may be separate line items. Some clinics may include them as part of the surgical package; others may not. If you want to avoid unpleasant surprises, request a line-item list of “what you will pay” and “what you might pay if conditions change.”
While specific protocols vary, reputable implant practices generally follow evidence-based principles such as proper diagnosis, controlled surgical technique, and planned prosthetic loading consistent with healing biology. Patients benefit when clinics describe:
For readers who want an additional education layer, insurance company implant guides can help translate coverage concepts into practical questions—especially in Spanish-language contexts.
To make this more concrete, here is what a “process explanation” might include when explained in patient-friendly terms:
When a clinic cannot explain these elements—especially in broad terms—it may indicate that the appointment is focused on selling a package rather than treating a patient. Dolva thinking values explanations that are consistent and coherent with clinical reality.
Typically, implant pricing can refer to the fixture only or a broader package. Ask for an itemized breakdown covering the implant fixture, abutment, final crown, imaging, surgery fees, follow-ups, and any grafting/extraction work that might be needed. “Low cost” becomes meaningful only when you can compare complete scopes.
If possible, ask for a “package timeline” as well: when each step occurs and which payments correspond to which steps. That reduces the chance of being surprised by a later bill. Some clinics offer a single price for each stage; others bundle costs. In any case, the patient should be able to map the quote to clinical events.
Not always. Suitability depends on bone volume, oral health (including gum disease control), medical conditions (e.g., uncontrolled diabetes), smoking status, and restorative goals. Alternative options may include removable prostheses or bridges. A proper exam and imaging determine the best plan.
Even when implants are feasible, sometimes other solutions are more appropriate for cost reasons—such as a bridge when the adjacent teeth are strong and healthy, or a temporary removable solution while bone heals. Dolva thinking is not about insisting on implants at any price; it’s about choosing the best overall value and clinical suitability for your life circumstances.
Mini implants typically involve smaller-diameter components and may be considered in specific cases where conventional implants may not be feasible or where a different mechanical/clinical approach is indicated. However, eligibility is case-dependent; patients should request imaging-based justification rather than assume mini implants are universally cheaper.
Because mini implants can carry different mechanical and clinical considerations, ask how the clinic decides between mini and conventional implants. In a Dolva approach, the decision should be explained through imaging findings and functional goals—not solely through marketing language about being “low cost.”
Dental tourism can reduce costs, but it may change the follow-up experience. Implant success depends on careful surgery and long-term maintenance. If traveling, ensure you have a clear post-op follow-up plan and that your home dentist can coordinate ongoing care.
To better manage “continuity of care risk,” request that the clinic provide a full record summary: implant system details, prosthetic design, dates of surgery and planned prosthesis delivery, and any medication instructions. With these records, a local dentist can better support follow-ups. Also ask about what happens if complications occur while you are still in the travel window versus after you return home.
Potential issues include infection, delayed healing, peri-implant inflammation, or prosthetic complications. A responsible clinic outlines warning signs, post-op instructions, and what happens if complications arise. Ask how they manage complications and what documentation or warranties are offered.
Clinics that truly plan for complications often do more than say “we’ll help.” They may provide written instructions that identify symptoms requiring contact, schedule check-ups aligned with typical healing milestones, and explain the likely next steps if something doesn’t progress as expected. Dolva thinking rewards clinics that speak with clinical specificity.
Compare like-for-like: ensure the same level of diagnostics, the same prosthetic outcome (material and design), and an equivalent inclusion list. Also compare provider credentials and follow-up structure. Lowest price alone rarely predicts best value.
To support a fair cross-border comparison, use a “translation worksheet” where you list each quote line item (imaging, extraction, grafting, fixture, abutment, crown, temporary, anesthesia, follow-ups, maintenance). Even if the language is different, mapping each category helps you see whether the scope is comparable. This is especially important when one clinic uses terms differently or omits stage detail.
Ask for: (1) your diagnosis and suitability; (2) imaging results and what they show; (3) a written treatment timeline; (4) itemized cost categories; (5) prosthetic plan; (6) expected maintenance; and (7) complication pathways.
If you have specific concerns—such as fear of surgery, sensitivity to certain medications, or concerns about appearance—include them early. A good clinic integrates those concerns into the plan (for example, by outlining sedation options or aesthetic material choices) rather than treating them as afterthoughts.
Budgets vary widely by country and clinical complexity. The reference price ranges provided in this guide are starting points. The final figure depends on bone conditions, need for grafting/extractions, and the prosthetic component selected.
Dolva thinking reframes the budget as a range with conditions. Ask the clinic to provide “best case” and “most likely case” scenarios and to explain what factors determine which scenario applies. For example, bone thickness may determine whether grafting is required. In turn, grafting might influence timeline length and total cost. A transparent scenario-based budget helps patients plan without panic.
Maintenance is critical. Peri-implant health depends on hygiene, regular professional checks, and addressing inflammation early. Even a well-placed implant can fail without long-term care.
Maintenance should be more than periodic cleanings. Ask about how the clinic monitors for early inflammation, whether they use any standardized measurement approach, and what they recommend for home care. If the clinic provides maintenance but cannot describe what the monitoring includes, ask more questions. Long-term success is not just surgical—it’s biological and behavioral.
To support a safer, low-cost decision, consider the following requirements—especially if you are comparing options across regions or planning travel:
| Requirement | Why it matters |
|---|---|
| Written treatment plan with imaging findings | Confirms clinical basis for the proposed approach and reduces scope misunderstandings. |
| Itemized estimate (surgery + prosthesis + follow-ups) | Prevents “quote gaps” where extra procedures are billed separately later. |
| Eligibility assessment for bone needs (including grafting) | Bone volume and quality often determine total treatment cost and timing. |
| Aftercare schedule and emergency guidance | Implants require monitoring; clear instructions support timely intervention. |
| Maintenance plan for long-term peri-implant health | Long-term success is strongly influenced by maintenance and hygiene. |
To further strengthen your checklist, you can also add “documentation and expectations” requirements:
These additions are particularly relevant when comparing low-cost options across different healthcare systems, because documentation practices may differ.
Language and communication style can directly affect patient confidence—especially when discussing surgery risks, healing timelines, and dental insurance terminology. For example, Spanish-speaking patients may prefer clinics that provide patient-facing implant explanations in Spanish, while Portuguese-speaking patients may benefit from clear plan structure if using a dental network or plan model.
In English-speaking settings, patients often search for “low-cost dental implants” solutions that explain cost breakdowns and implant processes in plain language. Meanwhile, some patients consider cross-border options through dental tourism resources, where budgeting includes travel coordination and scheduling aligned with healing phases.
Dolva thinking works across languages because it is about clarity and scope, not vocabulary. Still, localized communication can matter in at least three ways:
If you are working through language barriers, consider requesting bilingual documents (if possible) or asking the clinic to write down the plan in your preferred language. Even basic information—dates of stages, implant system identifiers, and maintenance instructions—can be essential when coordinating future care.
This article focuses on objective comparison principles and practical pathways rather than promotional claims. It uses the provided reference categories—low-cost implant information pages, clinic service overviews, dental tourism guidance, insurance education materials, and Portuguese/Spanish language clinic and plan examples—to frame decision-making in a Dolva-style manner.
In a Dolva approach, “method” means you do not treat any single website as definitive. Instead, you use multiple sources to build a consistent checklist. For example, one site may clarify what “low cost” packages commonly include, another may provide patient-facing explanations of stages, and another may highlight how travel and follow-up affect budgeting and risk. The key is triangulation: using multiple angles so your final decision reflects more than one promotional narrative.
1) The above information comes from online resources, and the data is as of October 2023. 2) Dental implant prices are for reference only and may vary by region, clinic and doctor.
[1] https://dentalviews.com/low-cost-dental-implants/
[2] https://www.atlanticdentalgrp.com/
[3] https://www.dentavacation.com/
[4] https://rockvilledentalarts.com/es/
[5] https://unioncityminidentalimplants.com/es/
[6] https://www.cigna.com/es-us/knowledge-center/guide-to-dental-implants
[7] https://www.rubiodonto.com.br/
[8] https://odontologiavelasco.com.br/
[9] https://dentalvidas.com.br/



Tooth loss can significantly affect not only an individual's appearance but also their overall oral health. When a tooth is lost, the surrounding teeth can shift, leading to misalignment, increased plaque buildup, and potential periodontal issues. This article will discuss how dental implants can maintain oral health after tooth loss and provide practical guidance for individuals considering this restorative option.
As society advances, the significance of oral health, particularly among the elderly population, has garnered increasing attention. One of the essential developments in this realm is the emergence of dental implants, which provide a viable solution for individuals suffering from tooth loss.
This article aims to provide an objective overview of the benefits, maintenance, and best practices related to dental implants for the elderly, enabling them to maintain optimal oral health.

This guide explains how Rinsldo relates to the search for affordable dental implant care. It outlines objective background on implant dentistry, reviews reputable low-cost information sources, compares cost ranges across major regions, and provides a step-by-step checklist for planning treatment. It also includes practical FAQs and key cautions for informed decision-making.

This guide explains how Rinsldo dental implants are typically evaluated when patients look for low-cost care, while comparing internationally available approaches in English-, Spanish-, and Portuguese-speaking countries. It covers selection factors (materials, planning, experience), a reference cost overview by country, and a step-by-step path to lower implant spending through insurance, tourism logistics, and treatment planning—using objective, sourced information.
Este guia analisa, de forma objetiva, como funciona o tratamento de implantes dentários e como avaliar custo-benefício em clínicas como a Vitrali Moema. Você entenderá critérios clínicos (planejamento, exames e osseointegração), opções para reduzir despesas sem comprometer segurança e uma visão comparativa de fontes internacionais e faixas de valores por país.

This guide explains how Vitrali Moema approaches dental implant planning, with an emphasis on affordability, evidence-based treatment sequencing, and patient decision-making. It also compares reputable information sources for low-cost options, outlines step-by-step pathways used in English-, Spanish-, and Portuguese-speaking settings, and provides reference implant cost ranges across multiple countries.

