This guide explains low-cost dental implants across English-, Spanish-, and Portuguese-speaking countries. It compares information sources, outlines practical steps to reduce costs without compromising safety, and provides reference price ranges by country and currency. It also clarifies how dental insurance plans and dental tourism options can affect affordability, with expert-focused FAQs and requirements.
Low-cost dental implants can make tooth replacement more attainable, but “low cost” can mean very different things depending on the clinic, country, and treatment model. Sometimes it reflects a streamlined process—fewer visits through improved diagnostic workflows, negotiated pricing, competitive materials sourcing, bundled care packages, or the convenience of receiving multiple services in one place. Other times, it reflects a reduction in the scope of what’s included, compressed timelines, limited diagnostic imaging, or less robust follow-up. Because implant success depends on clinical factors far beyond the implant fixture itself, the safest approach is to treat affordability as a value-optimization problem rather than a “lowest sticker price” problem.
From an expert perspective, affordability conversations should start with clinical eligibility and risk management. The implant is only one component of a long chain of decisions: bone quality and volume, gum health, infection control, implant system suitability, correct implant positioning, prosthetic design, occlusal planning, and long-term maintenance all influence outcomes. A “low-cost” offer that compromises any link in that chain can lead to complications that increase overall costs—such as additional procedures (bone grafting, soft-tissue revision), remakes of crowns, implant failure, or prolonged healing and downtime. Therefore, the most responsible goal is to reduce costs in ways that preserve evidence-based standards: clear diagnostic work, appropriate implant selection, reliable prosthetic planning, and a follow-up program that matches your risk level.
In this guide, you will find: (1) a comparison of websites that discuss low-cost dental implant topics, (2) step-by-step guidance for obtaining implants at lower cost across relevant regions, (3) reference cost ranges for single-tooth implants by country and currency, and (4) detailed FAQs to support objective decision-making. Beyond those sections, the guide expands on practical “check-before-you-sign” questions, how to interpret itemized estimates, how insurance and dental plan networks can change real out-of-pocket spending, and how mini implants may fit certain clinical situations.
When individuals search for terms related to low-cost dental implants, they are typically trying to balance three variables at the same time:
Websites such as Dental Views tend to frame affordability around transparent explanations of procedures, common questions, and factors that influence total pricing. The underlying value of educational content is that it helps patients differentiate between “cheap” and “cost-effective with safeguards,” especially by emphasizing that implants require more than a single surgical appointment.
Clinics like Atlantic Dental Group commonly present affordability as part of a broader service experience—cleanings, orthodontics, implant care, restorative dentistry, and emergency options. For many patients, the “true savings” come from reducing fragmentation: if you can complete pre-implant periodontal stabilization, extractions, and restorations inside one care pathway, you may avoid redundant assessments and scheduling delays that otherwise add cost.
For patients considering overseas treatment, platforms such as DentaVacation often emphasize cost comparisons and travel coordination. This can be helpful for budgeting, but it also means patients should be especially vigilant about documentation, warranties, and post-treatment follow-up when traveling back home.
For those who want cost control without leaving their local area, insurance-oriented resources associated with organizations like ADHP (or similarly structured guidance) tend to focus on coverage eligibility and application steps. Insurance can significantly reduce out-of-pocket spending, but coverage rules (waiting periods, documentation requirements, prior authorization, network limitations, and what counts as medically necessary) are often the real determinant of savings.
In short: “low-cost dental implants” in online resources usually refers to some mixture of pricing strategy and patient education, but the safest path is always to translate the marketing language into clinical specifics through an itemized estimate and a continuity-of-care plan.
Dental care markets vary widely by country, clinic infrastructure, regulatory environment, labor costs, implant supply chains, and insurance frameworks. Yet patients across regions repeatedly ask the same practical questions: “What will this include?” “Am I eligible for this option?” “What are the risks if I choose a lower-cost package?” and “What happens if something goes wrong?” These shared concerns make it possible to create a cross-region approach to affordability that remains clinically grounded.
In English-speaking markets, the conversation about implants often includes insurance networks, specialist referrals, and multi-step assessments. Many pathways also involve imaging like cone-beam CT (CBCT) when clinically appropriate, plus consultations with prosthodontic or surgical specialists depending on the case. Because systems can be more compartmentalized, clinics that provide a broader ecosystem of services—such as Atlantic Dental Group—may reduce barriers for patients who also require prerequisite treatment. If you need periodontal therapy before implant placement, extraction planning, or restorative work after implant integration, receiving those steps within one system can reduce delays that otherwise add time-related costs.
Pricing differences also arise from reimbursement models and the way clinics structure bundled services. In some settings, “low cost” offers appear as promotions or packages for the implant component, while still requiring separate fees for imaging, surgical guides, bone grafting, temporization, or restorative work. In other settings, the total cost is higher up front but may include follow-ups and warranty terms that are easier to access.
Spanish-speaking communities often rely on Spanish-language clinic information to make complex decisions more understandable. Rockville Dental Arts, for example, provides comprehensive services (including implants, whitening, cleaning, orthodontics, and emergency dental care) through a Spanish-focused interface designed to improve clarity and patient comfort. When clinic content is accessible, patients can ask sharper questions, understand what “included” actually means, and interpret treatment timelines more accurately.
Educational content from large healthcare and insurance organizations, such as Cigna, can also support better expectation management. Many implant complications arise from misunderstandings about what is “normal,” how long healing takes, or what symptoms require urgent contact. When patients understand the typical implant sequence—diagnostics, surgery, healing/integration, prosthetic fitting, and maintenance—they are more likely to comply with aftercare and attend follow-ups.
Some clinics specialize in implant approaches suited to specific scenarios. For example, Union City Mini Dental Implants highlights mini dental implants, which may be relevant in certain cases where implant placement requirements differ from conventional implants. The key for safety is ensuring that “mini” is a clinical match rather than a cost-cutting shortcut.
In Portuguese-speaking markets, affordability strategies frequently blend clinical pathways with insurance or dental coverage plans. Solutions offered by dental coverage providers such as DentalVidas can reduce routine and preventive costs, which indirectly supports implant readiness. This matters because implants are long-term; stable oral health, controlled gum disease, and effective hygiene routines reduce implant risk.
Clinics like Rubi Odonto and Odontologia Velasco generally present implant services alongside orthodontics, aesthetics, and restorative solutions. This matters because implant treatment is rarely isolated from other oral rehabilitation needs. A patient who is missing multiple teeth, has misalignment, or needs bite correction may require a sequence of steps that influences both cost and time.
In Brazil and Portugal, as in other markets, “low cost” can be associated with different implant systems, different prosthetic materials, and different clinical packages. Patients should therefore request written documentation of the implant brand/system, the abutment type, the planned crown material, the follow-up schedule, and the warranty terms.
This table compares the general type of information each site tends to provide around affordability, without treating any one page as a pricing authority or guaranteeing that an offer is safe in every circumstance. The value of comparing sources is to see how each site frames costs: whether it emphasizes clinical prerequisites, itemized estimates, continuity of care, insurance rules, or dental tourism logistics.
| Website (topic focus) | Main features related to low-cost implant decisions |
|---|---|
| Dental Views (low-cost implant education) | Explains implant benefits, treatment types, implant process, common FAQs, and cost-related considerations. |
| Atlantic Dental Group (clinic services + implant care) | Emphasizes a full range of dental services (including implants and emergency care) and appointment access. |
| DentaVacation (dental tourism affordability) | Supports international cost-saving narratives with procedure options, country comparisons, and travel coordination. |
| ADHP-related insurance guidance (insurance coverage) | Focuses on dental insurance plans, coverage options, application guidance, and how insurance can offset expenses. |
| Rockville Dental Arts (Spanish-language clinic information) | Provides implant services and related care in Spanish to improve comprehension for Spanish-speaking patients. |
| Union City Mini Dental Implants (mini implant specialization) | Highlights mini dental implants and the clinical situations they may address. |
| Cigna dental implant education (insurance/knowledge center) | Offers structured education on dental implants to help users understand treatment components. |
| Rubi Odonto / Odontologia Velasco (clinic services in Portuguese) | Present implant services within a broader scope including orthodontics, aesthetics, and restorative solutions. |
| DentalVidas (Portuguese-speaking dental plans) | Provides dental plan options and network-based access, potentially reducing preventive and some restorative costs. |
source list: [www.dentalviews.com](https://dentalviews.com/low-cost-dental-implants/) ; [www.atlanticdentalgrp.com](https://www.atlanticdentalgrp.com/) ; [www.dentavacation.com](https://www.dentavacation.com/) ; [rockvilledentalarts.com/es](https://rockvilledentalarts.com/es/) ; [unioncityminidentalimplants.com/es](https://unioncityminidentalimplants.com/es/) ; [www.cigna.com/es-us/knowledge-center/guide-to-dental-implants](https://www.cigna.com/es-us/knowledge-center/guide-to-dental-implants) ; [www.rubiodonto.com.br](https://www.rubiodonto.com.br/) ; [odontologiavelasco.com.br](https://odontologiavelasco.com.br/) ; [dentalvidas.com.br](https://dentalvidas.com.br/)
Below is a practical, patient-centered pathway for obtaining implants at lower cost in English-, Spanish-, and Portuguese-speaking countries. The steps are designed to reduce unnecessary expense while preserving safety and long-term outcomes.
Throughout the steps, keep one principle in mind: you can often reduce cost either by (a) lowering complexity (when clinically appropriate), (b) negotiating or optimizing pricing for included services, or (c) improving access to financing and insurance benefits. You should avoid reducing cost by accepting incomplete diagnostics, insufficient follow-up, unclear warranties, or prosthetic designs that don’t support maintenance.
Before comparing clinic prices, confirm whether you are a candidate for an implant plan that fits your anatomy and health status. Eligibility is often the biggest determinant of total cost because it affects whether you need additional procedures.
Expert note: Many patients experience “surprise costs” because the initial estimate didn’t account for grafting, extractions, periodontal therapy, temporary solutions, or specific prosthetic materials. Surprise costs are not automatically a “bad clinic” sign—sometimes they reflect the fact that diagnostics were incomplete—but they are a predictable failure point when “low cost” is offered without adequate clinical evaluation.
When comparing clinics, compare components rather than final totals. Two clinics may quote different prices for very different packages, or they may quote similar totals but include different materials, different levels of diagnostic detail, or different warranty terms.
Consider comparing the following categories:
Practical tip: Request quotes in writing and ask clinics to “match” the scope. For example, if Clinic A’s estimate includes grafting and Clinic B’s does not, that doesn’t make Clinic B cheaper—it makes the cases incomparable.
For many patients, the lowest price is not always the best value. The best value often comes from combining competitive pricing with coverage that reduces out-of-pocket spending—especially for diagnostic work, pre-implant periodontal therapy, and restorative stages after integration.
Insurance-related “hidden” factors to ask about:
Clinics offering a broad service range—such as Atlantic Dental Group—can reduce fragmentation. If you need additional work (periodontal therapy, extractions, orthodontic alignment, or emergency dental care), completing those prerequisites in one system can streamline scheduling and reduce redundant assessments.
Bundling can lower costs in several ways:
However, bundling must not replace specialized expertise. If you need complex surgery (e.g., significant grafting, sinus augmentation, or advanced prosthetic planning), ensure that the clinic has the appropriate specialist skills and that the treatment plan is evidence-based.
Websites like DentaVacation may discuss cost savings through traveling abroad. Cost reductions may occur, but your decision should include critical safeguards.
Expert note: Implant systems involve long-term outcomes. The “true cost” includes the possibility of additional visits, remakes, or complication management. A plan that is inexpensive abroad can become expensive if follow-up care is difficult to access afterward.
Additional dental tourism safeguards: Ask whether they will provide a treatment letter that your local dentist can use. Ask whether they will schedule at least the earliest post-operative checkpoints (e.g., early follow-up after placement and suture checks, if relevant) before you leave. Also ask about antimicrobial prescriptions, hygiene instructions, and emergency contact procedures.
Installment plans and staged payments can lower the immediate burden, but you should not let finance options mask scope reductions. Financing is a timing tool; it does not replace clinical necessities like adequate diagnostics, healing time, infection control, and proper prosthetic fit.
Questions to ask before signing finance agreements: What portion of the fee is refundable if complications occur? Are there penalties for missing follow-up visits? Does the finance plan require you to use specific clinics or follow-ups? These questions matter because sometimes “low cost” financing is paired with limited continuity.
Even when the price is reduced, outcomes depend on adherence to aftercare and on receiving appropriate follow-ups. A low-cost plan can still succeed if the clinical standards are preserved and the patient complies with instructions.
Behavior and lifestyle factors: Smoking and uncontrolled diabetes can significantly impact healing. If your clinic has a pre-surgery readiness checklist, ask about modifications you can make before surgery—these can sometimes reduce risk without adding cost.
The following ranges are for individual dental implants (single-tooth replacement), expressed in the currencies commonly used in each market. Actual pricing may differ depending on the need for bone grafting, implant system selection, crown material, clinic overhead, diagnostic complexity, and whether temporization is included.
| Country | Currency | Price range for a single implant (reference) |
|---|---|---|
| United States (nearby) | USD | $3,000 - $6,000 |
| United Kingdom (nearby) | GBP | £2,000 - £2,500 |
| Australia (nearby) | AUD | AU$3,500 - AU$6,500 |
| Canada (nearby) | CAD | CA$3,000 - CA$5,500 |
| Spain (nearby) | EUR | €1,500 - €2,500 |
| Chile (nearby) | CLP | CLP$800,000 - CLP$1,500,000 |
| Mexico (nearby) | MXN | $15,000 - $25,000 MXN |
| Colombia (nearby) | COP | $2,000,000 - $4,000,000 COP |
| Peru (nearby) | PEN | S/ 3,000 - S/ 6,000 |
| Argentina (nearby) | ARS | $80,000 - $150,000 ARS |
| Brazil (nearby) | BRL | R$3,000 - R$8,000 |
| Portugal (nearby) | EUR | €1,000 - €2,000 |
How to interpret these ranges safely: Treat them as reference starting points, not guarantees. If a quote is far below the reference range, ask why. If the difference is explained by a genuinely different scope (e.g., no grafting needed, fewer appointments because temporization is simplified, or an included warranty), it may still be reasonable. If the explanation is vague, or if essential components are excluded, the low price may hide costs or risks.
What can swing costs up or down: bone grafting (minor vs major), sinus lift, the number of appointments, the use of guided surgery, the quality and type of abutment, the crown material, the complexity of occlusion (especially in front teeth vs back teeth), and the need for additional soft tissue procedures such as connective tissue grafting.
In professional practice, cost reduction should not compromise clinical essentials. When an expert reviews a “low-cost implant” offer, they typically scrutinize both what is included and what is missing.
An objective review often focuses on:
Specific items to insist on clarifying:
Specialized clinics such as Union City Mini Dental Implants highlight mini dental implants. Mini implants can be appropriate for selected patients depending on anatomy, stability needs, and prosthetic design. The crucial point for affordability is that suitability drives outcome—not the size label alone.
Why mini implants can sometimes be cheaper: In some clinical scenarios, mini implants may reduce the complexity of the prosthetic construction, or they may be chosen when sufficient bone is limited in a way that makes certain conventional implant strategies more challenging. Additionally, some approaches may reduce the need for extensive components depending on the prosthetic plan.
Why mini implants are not automatically “better value”: If mini implants are selected for a case that does not match their mechanical and prosthetic requirements, the likelihood of complications such as prosthetic loosening, discomfort, or the need for redesign may increase. This can lead to extra visits and potential replacement costs that negate the initial savings.
Safety-focused evaluation for mini implants: ask the clinic how mini implants are justified for your anatomy. Ask about occlusion planning, connector design, hygiene accessibility, and what their monitoring schedule looks like. Also ask whether there is an option to proceed with conventional implants if mini implants are not predicted to meet stability and long-term function needs.
Mini implants in a “low-cost” context: If a low-cost offer uses mini implants to reduce cost, confirm that the plan is clinically appropriate for your specific tooth position (front vs back), your bite forces, and your expected prosthetic use. For some patients, a mini implant plan may be a reasonable cost-effective strategy; for others, it may be a short-term solution that requires future correction.
Below is an objective “conditions and requirements” checklist. It helps patients understand what must be clarified before signing an agreement for an implant at a reduced price.
Extra risk questions that often prevent regret:
It usually refers to a combination of factors: clinic pricing, bundled procedures, treatment planning efficiency, and sometimes insurance or financing structures. The most reliable way to evaluate “low cost” is to compare itemized quotes and determine what is included (implant placement, abutment, crown, imaging, and follow-ups). If the offer does not itemize these elements, treat it as incomplete information rather than a true cost comparison.
In practical terms, a quote should ideally list: consultation and diagnostic imaging, surgical placement fees, implant and abutment fees, crown or prosthetic fees (and whether temporary work is included), additional procedures such as grafting or periodontal treatment, and scheduled follow-ups during both healing and prosthetic delivery stages.
Not automatically. Quality depends on clinical planning, materials, and follow-up—not only price. However, unusually low offers can be a warning sign if they omit necessary diagnostics, compress healing periods, or fail to provide clear warranty and aftercare. The key is to ask what changes: which specific components are cheaper, what is excluded, and how follow-up is handled.
For example, a clinic might reduce costs by using an efficient workflow while still performing adequate diagnostics and offering a robust maintenance schedule. Another clinic might reduce costs by charging less for the implant and then excluding key services such as temporization, imaging, or occlusal adjustments.
Costs vary due to labor differences, regulatory environments, implant supply chains, clinic overhead, and insurance or financing structures. In addition, some countries have different standard practices around diagnostic imaging frequency, lab fees for crowns, and appointment models (longer initial consultations vs shorter procedural visits). Complex procedures included (or excluded) in a quote—such as grafting, sinus lifts, or soft-tissue procedures—also influence total costs.
Additionally, implant systems and prosthetic lab processes may differ. Even if the implant fixture cost is similar, the crown fabrication method and material selection can change the final cost.
In many insurance structures, implants may have partial coverage, waiting periods, or specific eligibility rules. Insurance guidance pages (for example, resources aligned with ADHP-style guidance) commonly emphasize checking coverage terms, pre-authorization requirements, and in-network providers.
Whether insurance helps depends on the policy: some plans cover preventive care but have limited implant reimbursement; others may partially reimburse implants when deemed medically necessary. Also, insurers may reimburse different components differently: implant fixtures versus crowns versus surgical adjuncts.
Practical step: before scheduling, request a breakdown of what the insurer would cover and what documentation is needed. Ask the clinic’s billing office what codes they typically submit and whether prior authorization is commonly required.
It can reduce costs for some patients, as platforms like DentaVacation describe cost-saving options and travel coordination. Still, expert practice emphasizes verifying post-treatment support, documentation, warranty terms, and your ability to obtain follow-up care after returning.
Dental tourism can be especially risky if you cannot access local expertise for managing complications. If your return home is far from any supportive provider, ask local dentists whether they will monitor the implant and manage common follow-up issues (soreness, inflammation, prosthetic adjustments). Make sure you can bridge the care gap after you travel.
Minimum documentation to request before leaving abroad: implant brand/system, lot/batch numbers, date of placement, surgical notes, prosthetic component details, and a follow-up schedule. Documentation helps continuity and can reduce delays if problems arise.
Bone grafting can add time and cost. It is a common clinical requirement when bone volume is insufficient. From a cost-control standpoint, the best approach is to request imaging-based eligibility assessment before comparing prices. If grafting is likely, compare clinics based on what they include: type of graft, whether it’s done simultaneously with implant placement or staged, and what the follow-up schedule looks like.
Ask also whether grafting success rates vary by case complexity and whether the clinic has experience with your specific graft situation. For many patients, the cost-effective approach is to prevent grafting surprises by clarifying eligibility earlier.
Timelines vary by case. Healing and osseointegration periods depend on bone quality, implant positioning, and whether additional procedures are required. Your clinician should provide a planned timeline tied to your diagnosis rather than a generic estimate.
In general terms, the implant must integrate with bone before the final crown is placed. In some protocols, temporary teeth may be placed sooner if clinically appropriate, but this depends on primary stability and the restorative plan. Ask your clinic how they handle temporization for your case and whether the temporaries are included in the quote.
They may be less expensive in selected cases, particularly if they reduce certain prosthetic complexity. However, suitability is crucial. A mini implant approach should match anatomy and functional requirements. If mini implants are appropriate, a more streamlined plan could reduce costs. If not, costs can rise later due to redesign or complications.
When deciding, ask about the planned prosthetic design (and whether it will be removable, fixed, or hybrid), the occlusion plan, and how hygiene will be maintained at the implant interface. Mini implants are not a one-size-fits-all cost reduction method.
Ask for a written, itemized breakdown and explicitly confirm whether the quote includes: imaging, implant placement, abutment, crown fabrication, temporary solutions, and follow-up visits. Also ask what additional procedures could change the price.
Hidden costs often appear in these categories:
To avoid surprises, ask clinics to define their inclusion criteria. For example: “If grafting is required, is there a predetermined package price?” or “If my case requires additional visits, what are the hourly or per-visit fees?”
True cost typically includes diagnostic work, surgical and prosthetic fees, required bone or gum procedures, maintenance visits, and the potential for corrective work. For long-term outcomes, aftercare and hygiene support are part of the total value assessment.
It also includes the cost of time: additional visits for healing checks, prosthetic adjustments, or management of complications. Even if you personally pay little for the initial implant fixture, the overall cost can rise if you need additional corrective work.
When calculating “true cost,” consider these categories:
If your goal is affordability, use this framework:
Because language and access can influence decision quality, incorporate region-specific considerations:
Additional affordability strategy: Ask if the clinic offers alternative pathways when complexity is reduced. For example, if you are missing a tooth but have adequate bone, you may be a candidate for a more straightforward approach. If bone is deficient, clarifying whether the plan includes grafting (and whether grafting can be staged) can affect both price and timeline. When properly planned, staging can reduce risk and prevent emergency add-ons later.
Low-cost dental implants are achievable for many patients, but responsible affordability requires more than comparing a price range. The most objective approach is to identify your clinical requirements, demand transparent itemized quotes, evaluate insurance or plan options, and—if considering dental tourism—confirm continuity of care and the availability of follow-up support.
By applying these steps across English-, Spanish-, and Portuguese-speaking countries, patients can reduce the risk of cost-related surprises while supporting outcomes that matter long term: stable implant integration, well-designed prosthetics that support hygiene, and maintenance plans that protect the investment.
Ultimately, the safest definition of “low cost” is not “the cheapest quote.” It is “the best total value for your specific clinical needs,” including the cost of diagnostics, the cost of necessary pre-treatment, the cost of a durable prosthetic design, and the cost of follow-up that protects you after you’ve healed.
1) The above information comes from online resources, and the data is as of October 2023. 2) Dental implant prices are for reference only and may vary by region, clinic and doctor.
https://dentalviews.com/low-cost-dental-implants/
https://www.atlanticdentalgrp.com/
https://www.dentavacation.com/
https://rockvilledentalarts.com/es/
https://unioncityminidentalimplants.com/es/
https://www.cigna.com/es-us/knowledge-center/guide-to-dental-implants
https://www.rubiodonto.com.br/



Tooth loss can significantly affect not only an individual's appearance but also their overall oral health. When a tooth is lost, the surrounding teeth can shift, leading to misalignment, increased plaque buildup, and potential periodontal issues. This article will discuss how dental implants can maintain oral health after tooth loss and provide practical guidance for individuals considering this restorative option.
As society advances, the significance of oral health, particularly among the elderly population, has garnered increasing attention. One of the essential developments in this realm is the emergence of dental implants, which provide a viable solution for individuals suffering from tooth loss.
This article aims to provide an objective overview of the benefits, maintenance, and best practices related to dental implants for the elderly, enabling them to maintain optimal oral health.
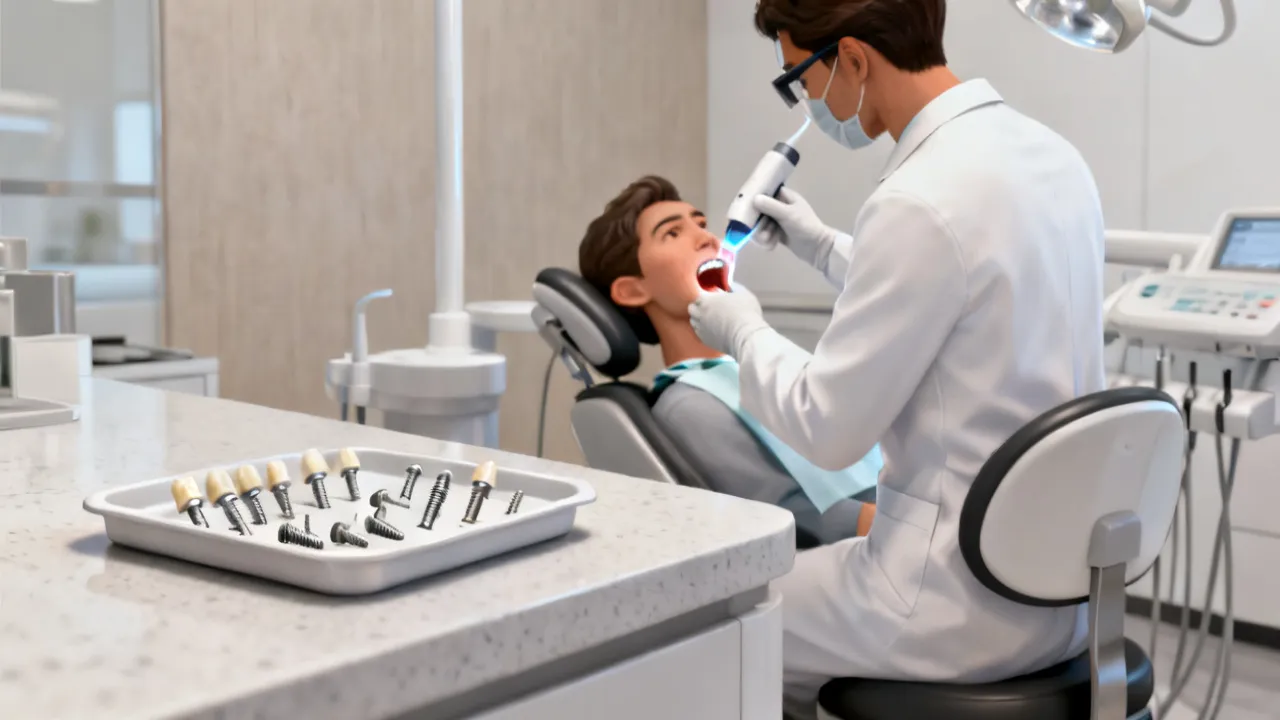
This guide explains how Elinlza teuezada and saliva relate to dental implant planning, especially when you are pursuing low-cost dental implants. It reviews how saliva affects oral health, why clinicians assess it alongside implant readiness, and how to compare reputable sources, estimate implant cost ranges, and follow a step-by-step pathway in English-, Spanish-, and Portuguese-speaking regions.
Esta guía analiza, con enfoque clínico y objetivo, la relación entre Elinlza teuezada y la saliva, y cómo influyen en la salud oral. También revisa opciones de implantes dentales de bajo costo en países hispanohablantes, describe rangos de precios orientativos y ofrece un proceso paso a paso para tomar decisiones informadas.

This guide explains how dental implants are planned and how saliva-related health factors can influence comfort and healing. It also reviews affordability strategies, including low-cost implant options across English-, Spanish-, and Portuguese-speaking regions, plus practical cost expectations and selection criteria. The keywords “Elinlza teuezada., Saliva” are addressed in an objective clinical context.
Esta guía analiza, con enfoque profesional, la relación entre Elinlza teuezada y la saliva en salud bucal. Se explican causas frecuentes de alteraciones salivales, su impacto en la higiene y el tratamiento, y cómo valorar opciones como implantes dentales de menor costo. Incluye rangos orientativos por país, pasos para cotizar y un apartado de preguntas frecuentes.

